Lumbar Canal Stenosis (LCS): Causes, Symptoms & Treatment
A comprehensive medical guide to understanding spinal canal narrowing, neurogenic claudication, associated nerve compression, precise diagnostics, and targeted non-surgical treatment options.
Book Free Consultation
Enter your details and our senior medical coordinator will reach out.
Recognising the Classic Pattern
Lumbar canal stenosis has a distinctive symptom pattern that helps confirm the diagnosis: pain, heaviness, or cramping in the legs that appears or worsens with standing and walking (neurogenic claudication), and eases when sitting down or bending forward.
This happens because standing and walking narrow the spinal canal further, while sitting or forward bending opens it up and relieves pressure on the nerves. Our clinic provides thorough clinical evaluation and progressive rehabilitation to restore comfortable walking tolerance.
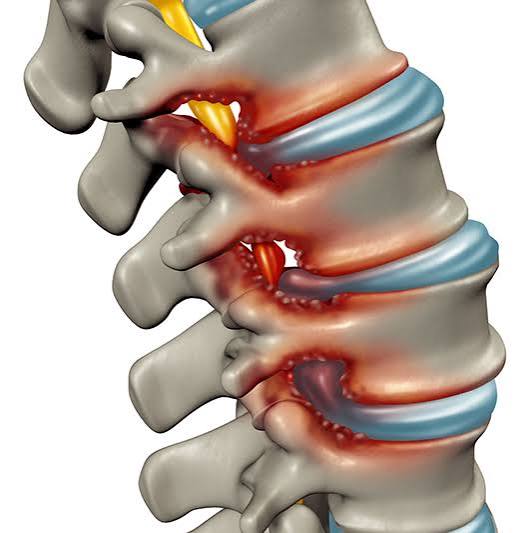
Common Symptoms of Lumbar Canal Stenosis
Do not ignore these physical red flags associated with neurogenic claudication and nerve compression:
Radiating Pain
Lower back pain that spreads into the buttocks or legs during standing.
Walking Heaviness
Leg cramping, heaviness, or numbness while walking or standing (neurogenic claudication).
Flexion Relief
Pain that eases when sitting down or bending forward over a shopping cart or bike.
Burning Sensation
Tingling or a burning sensation felt in the legs or feet during activity.

What Causes Spinal Canal Narrowing?
Spinal stenosis stems from age-related degeneration, bone spurs, and ligament thickening:
- Age-Related Degeneration: Wear and tear of spinal discs and facet joints over time.
- Thickened Ligaments: Ligamentum flavum thickening and pressing into the spinal canal.
- Bone Spurs: Osteophyte overgrowths from osteoarthritis narrowing the central canal space.
- Disc Bulges & Spondylolisthesis: Disc herniations or vertebral slippage adding mechanical pressure on nerves.
Treatment Strategy & Rehabilitation Protocols
Exercises for lumbar canal stenosis deliberately favour gentle flexion (forward-bending) positions over extension, since bending forward is what naturally relieves symptoms:
Pain-Relief and Decompression Modalities
- TENS: Eases pain signals during the early, most uncomfortable stage.
- Low-level laser therapy: Supports healing in irritated tissue around the spine.
- Hot pack therapy: Relaxes tight muscles before movement-based treatment.
- Lumbar decompression therapy: Gently increases the space within the spinal canal to reduce pressure on compressed nerves.
- Focused shockwave therapy: Targets deep soft tissue and tight paraspinal muscles.
Manual Therapy
- Soft tissue mobilisation: Releases tight muscles around the spine and hips that add to nerve compression.
- Rhythmic spinal glides: Restore normal movement between vertebral segments.
- Core and postural positioning: Training the spine to stay in a neutral or slightly flexed posture, which widens the canal and reduces nerve pressure.
Exercise Programme
- Core flexion and stretching: Double knee-to-chest stretch, seated forward flexion, posterior pelvic tilts, core and glute activation.
- Strength and aerobic conditioning: Glute bridging within a comfortable range (avoiding overextension), modified bird-dog without arching the back, static cycling, graded oblique exercises, and seated iliopsoas-targeted work.
Movements to Avoid
- Spinal extension exercises, which narrow the canal further and can worsen symptoms.
- Heavy weight lifting, squats, and deadlifts.
- Lying flat on the stomach, which places the spine in extension.
How Lumbar Canal Stenosis Is Diagnosed
Our structured 4-tier comprehensive diagnostic protocol maps over 80 specific clinical history, physical testing, and neuroimaging parameters for precise stenosis care.
1. Medical History & Claudication
Detailed recording of walking distance limits, leg heaviness, and flexion relief.
- Neurogenic Claudication: Measuring exact walking distance before leg cramping or weakness forces rest.
- Shopping Cart Sign: Checking if leaning forward over shopping carts or bikes relieves leg pain.
- Bicycle Test: Evaluating ability to ride stationary bike without pain despite upright walking limits.
- Leg Heaviness: Recording fatigue and rubbery sensation in thighs and calves during standing.
- Numbness & Paresthesia: Mapping pins and needles distribution across lower limbs and soles.
- Pain Onset Profile: Determining gradual progression of spinal narrowing over years.
- Age & Degeneration Factor: Reviewing age-related facet hypertrophy and ligament thickening.
- Sitting vs Standing: Documenting pain freedom while seated compared to upright posture.
- Stair Climbing Tolerance: Recording discomfort going up versus down stairs.
- Previous Spinal Surgeries: Screening for prior laminectomies or fusion procedures.
- Balance & Stability Reports: Evaluating unsteadiness or tripping hazards during walks.
- Night Pain Check: Determining if spinal position affects resting comfort.
- Cauda Equina Screen: Checking emergency red flags for bladder or bowel control loss.
- Previous Treatment Review: Recording response to past physical therapy or epidural injections.
- Activity Restriction Log: Assessing limitations on community outings and hobbies.
- Comorbidity Screen: Evaluating vascular health to rule out vascular claudication.
- Symptom Progression Rate: Tracking decline in functional walking capacity.
- Pain Severity Scoring: Rating daily lower back and leg distress levels.
- Symptom Triggers: Identifying specific factors worsening nerve compression.
2. Physical Examination
Hands-on neurological testing, extension loading, and balance evaluation.
- Lumbar Extension Test: Provoking stenosis symptoms by leaning spine backward.
- Flexion Relief Test: Confirming symptom reduction when patient bends forward.
- Treadmill Stress Test: Monitoring functional walking collapse on inclined treadmill.
- Deep Tendon Reflexes: Testing patellar and Achilles tendon responses.
- Myotome Power Screening: Assessing muscle strength in foot dorsiflexion and extension.
- Dermatome Sensation Test: Checking light touch and pinprick across lower extremity fields.
- Straight Leg Raise Test: Checking nerve root tension and stretch tolerance.
- Romberg Balance Test: Evaluating proprioception and dorsal column function.
- Toe and Heel Walking: Screening for L4, L5, and S1 motor root weakness.
- Peripheral Pulse Check: Palpating pedal pulses to rule out vascular claudication.
- Spinal Range of Motion: Measuring flexion and extension restrictions.
- Posture & Alignment Check: Observing flattened lumbar lordosis or stooped stance.
- Palpation Screening: Checking for tenderness and secondary muscle guarding.
- Hip Joint Examination: Screening for co-existing hip osteoarthritis or stiffness.
- Vascular Reflex Check: Assessing capillary refill and skin temperature in feet.
- Functional Mobility Assessment: Observing speed and endurance during physical exam transitions.
- Core Stability Screen: Evaluating trunk control under fatigue.
- Gait Observation: Checking wide-based or unsteadied walking patterns.
- Physical Summary: Compiling examination metrics.
3. Imaging & Differential Evaluation
MRI scans, standing X-rays, vascular screening, and differential diagnosis.
- MRI Scan (Gold Standard): Visualizing neural sac compression, facet hypertrophy, and ligamentum flavum buckling.
- Standing Lumbar X-Rays: Evaluating alignment, spondylolisthesis slips, and disc space height.
- CT Scan with Myelogram: High-resolution bone and contrast-enhanced canal visualization.
- Flexion-Extension X-Rays: Assessing dynamic instability contributing to canal narrowing.
- Electromyography (EMG): Testing nerve-to-muscle electrical conductivity to confirm radiculopathy.
- Nerve Conduction Studies (NCS): Measuring nerve signal velocity across lumbar segments.
- Vascular Doppler Ultrasound: Ruling out peripheral arterial disease (vascular claudication).
- Canal Area Measurement: Calculating cross-sectional dural sac area on MRI axial slices.
- Facet Arthropathy Grading: Assessing joint enlargement contributing to posterior stenosis.
- Differential Diagnosis: Distinguishing neurogenic claudication from vascular claudication or peripheral neuropathy.
- Blood Inflammatory Tests: Running ESR and CRP to rule out systemic infection or tumor.
- Bone Density Scan (DEXA): Screening for osteoporosis in older adults.
- Surgical Consultation Review: Assessing candidacy for decompression surgery in severe cases.
- Digital Record Archiving: Secure cloud storage of radiological reports.
- Specialist Peer Review: Multi-expert consensus on canal management.
- Risk Stratification: Assessing nerve root compromise levels.
- Prognosis Review: Estimating functional walking timelines.
- Lab Correlation: Matching systemic blood markers.
- Diagnostic Confirmation: Final report formulation.
4. Treatment & Recovery Plan
Flexion-based physical therapy, neural decompression care, and lifestyle adaptation.
- Flexion-Based Exercises: Prescribing posterior pelvic tilt and knee-to-chest routines to open spinal canal space.
- Stationary Cycling Training: Utilizing recumbent bikes to maintain cardiovascular fitness without upright stenosis symptoms.
- Manual Spinal Decompression: Gentle manual traction to relieve posterior element crowding.
- Core Stabilization Training: Strengthening abdominal support to maintain a slightly flexed, comfortable posture.
- Posture & Walking Pacing: Teaching patients how to use intermittent rest intervals during community walks.
- Pain Management Modalities: Non-invasive therapies to soothe neurogenic inflammation.
- Epidural Steroid Coordination: Referring for targeted anti-inflammatory injections when conservative therapy plateaus.
- Home Exercise Program: Custom daily stretching regimens for lower back and hip mobility.
- Activity Modification: Advising on posture adjustments during standing chores and cooking.
- Ergonomic Seating Advice: Optimizing support for comfortable sitting and resting.
- Milestone Progress Tracking: Weekly clinical evaluations measuring walking tolerance gains.
- Regular Clinical Follow-ups: Ongoing monitoring with senior care coordinators.
- Patient Self-Care Briefing: Clear instruction on utilizing sitting rests during flare-ups.
- Long-Term Protection Strategy: Preserving functional independence and mobility.
- Maintenance Care Routines: Sustaining spinal health post-rehabilitation.
- Re-injury Prevention: Balance and stability training to avoid falls.
- Mobility Enhancement: Safe hip and thoracic movement preservation.
- Specialist Consult Coordination: Managing surgical evaluations if severe motor deficits arise.
- Active Lifestyle Clearance: Final approval for optimized daily community activities.
Meet Our Experts
Get guidance for Sacralisation and Lumbarisation, spinal conditions involving variations in the structure of the lower spine. Our care approach focuses on understanding individual spinal anatomy, managing lower-back discomfort, improving mobility, and supporting everyday activities through a personalised assessment and rehabilitation plan.
Ask Our Specialist
Our approach to sacralisation and lumbarisation focuses on understanding your spinal structure, addressing movement-related discomfort, and supporting lower-back mobility. Your care plan is tailored to your individual symptoms and functional needs, with appropriate movement guidance and rehabilitation to help improve comfort and everyday activities.
Patient Success Stories
Watch real recovery stories from patients who regained their active lifestyles.
Patient Recovery Story
Real experiences. Better mobility.
Patient Recovery Story
Real patient experiences and recovery journeys.
Frequently Asked Questions
Clear answers to common clinical questions about lumbar canal stenosis, causes, and treatments.