Cervicogenic Headache: Causes, Symptoms & Treatment
A specialized medical guide to understanding neck-derived headaches, shared nerve pathways, diagnostic evaluation pathways, and targeted therapeutic management.
Book Free Consultation
Enter your details and our senior medical coordinator will reach out.
What Is a Cervicogenic Headache?
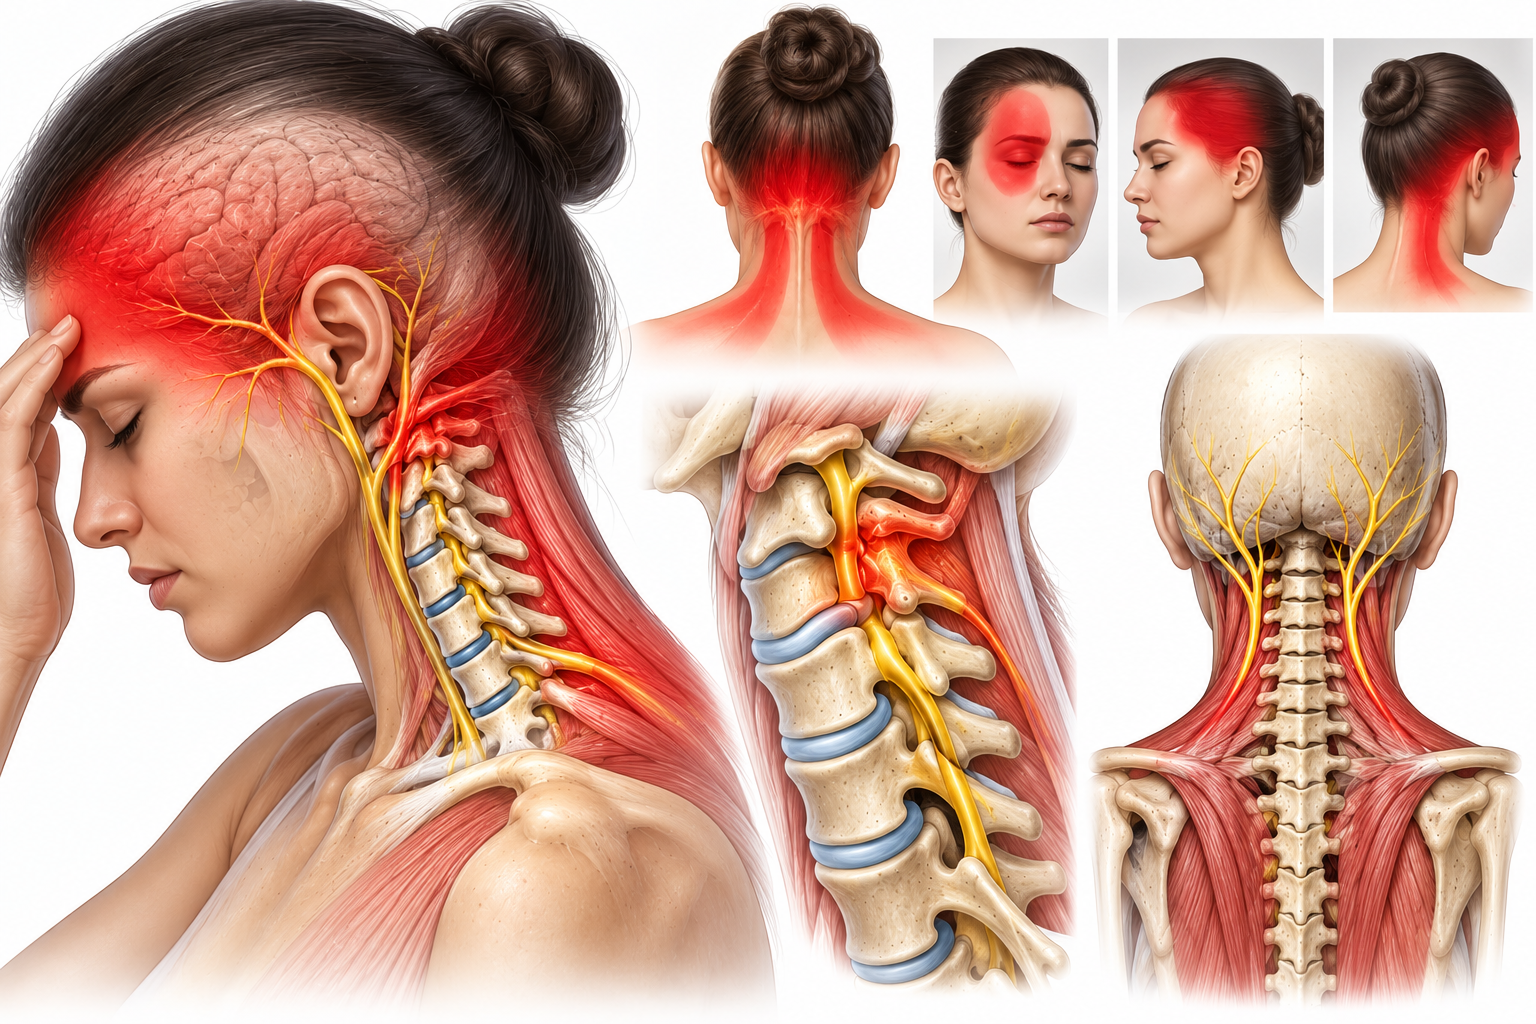
A cervicogenic headache is head pain that actually originates in the neck rather than the head itself.
Problems in the cervical spine — its joints, discs, or muscles — refer pain upward through shared nerve pathways, creating a headache that can easily be mistaken for a migraine or tension headache. Recognising the neck as the true source is key to getting the right treatment.
Common Symptoms of Cervicogenic Headaches
Do not ignore these physical signs indicating upper cervical spine nerve referral into the head:
Suboccipital Ache
A steady, dull ache starting at the base of the skull and spreading to one side of the head.
Movement & Posture Trigger
Pain that worsens with certain neck movements, poor posture, or prolonged sitting.
Restricted Range of Motion
Reduced neck range of motion accompanying the cervicogenic headache.
Referred Facial Pain
Pain radiating to the forehead, temple, or around one eye, alongside shoulder or arm discomfort.

What Causes Cervicogenic Headaches?
Neck-related head pain originates from upper cervical convergence and mechanical joint irritation:
- Poor Posture ("Tech Neck"): Prolonged forward head position from screen use straining the cervical spine.
- Cervical Spondylosis: Age-related neck arthritis and degenerative joint wear in the upper cervical spine.
- Whiplash or Trauma: Previous neck trauma or whiplash injury straining upper cervical ligaments.
- Muscle Tension: Tightness and myofascial trigger points in the neck and upper shoulders.
Treatment Approaches & Management
Resolving cervicogenic headaches centers on manual therapy, postural correction, and deep neck flexor training:
Manual Therapy & Posture
Physiotherapy targeting neck mobility, posture, manual therapy, and targeted neck stretching exercises.
Ergonomics & Injections
Ergonomic workstation adjustments, heat therapy, pain-relief medication, and trigger point or nerve block injections for persistent cases.
How Cervicogenic Headaches Are Diagnosed
Our structured 4-tier clinical diagnostic protocol evaluates flexion-rotation test (FRT) range limits, upper cervical facet joint tenderness, migraine/tension headache differentials, and diagnostic medial branch blocks.
1. History & Neck Pain Trigger Audit
Detailed screening of suboccipital headache start, desk posture strain, neck movement triggers, and unilaterality.
- Suboccipital Pain Initiation: Documenting headaches that consistently start at the base of the skull (occiput) and spread forward.
- Unilateral Side Dominance: Tracking whether head pain remains strictly on the same side as neck stiffness.
- Sustained Computer Desk Strain: Correlating afternoon headache intensity with hours spent looking at monitors with forward head posture.
- Neck Movement Provocation: Recording headache worsening when turning the head or holding awkward neck angles.
- Prior Whiplash Trauma Audit: Screening for historical motor vehicle collisions or sports tackle neck hyper-extension.
- Absence of Autonomic Symptoms: Confirming lack of severe throbbing nausea, photophobia, or visual aura (ruling out classic migraine).
- Manual Pressure Reproduction: Inquiring if pressing on upper neck joints reproduces the exact headache.
- Sleep Pillow Ergonomics Audit: Assessing whether neck support pillows reduce morning waking stiffness and headaches.
- Smartphone "Text Neck" Usage: Evaluating hours spent looking down at handheld devices daily.
- Medication Overuse Evaluation: Checking frequency of analgesics taken for headaches (ruling out rebound medication headaches).
- Stress & Jaw Clenching Screen: Screening for co-existing temporomandibular joint (TMJ) grinding and suboccipital tension.
- Visual Analog Scale (VAS) Baseline: Recording headache frequency, duration, and intensity scores (0-10 scale).
- Baseline Headache Disability Inventory: Measuring functional impact on daily work and personal life.
2. Headache Classification & Red-Flags
Differentiating cervicogenic headaches from migraines, tension-type headaches, cluster headaches, and intracranial pathologies.
- Migraine Without Aura Differentiation: Differentiating pulsating, nausea-inducing migraines from neck-driven cervicogenic pain.
- Tension-Type Headache Comparison: Distinguishing band-like bilateral tension headaches from unilateral neck-origin headaches.
- Cluster Headache Exclusion: Ruling out excruciating periorbital pain with ipsilateral eye watering and nasal congestion.
- Intracranial Mass / Tumor Red-Flag Screen: Screening for "thunderclap" onset, papilledema, vomiting, and progressive neurological deficits.
- Temporal Arteritis (Giant Cell Arteritis): Screening older adults (>50 yrs) for scalp tenderness, jaw claudication, and elevated ESR.
- Cervical Artery Dissection Red-Flag: Screening sudden neck pain and headache with ipsilateral Horner's syndrome (emergency triage).
- Meningitis & Infection Screen: Ruling out fever, stiff neck, and photophobia requiring immediate lumbar puncture.
- Trigeminal Neuralgia Differentiation: Differentiating electric shock facial nerve pain from upper cervical somatic pain.
- Occipital Neuralgia Differentiation: Identifying shooting pain directly along greater/lesser occipital nerve distributions.
- Complete Neurological Examination: Confirming normal cranial nerves, normal motor strength, and normal reflexes.
- Urgent Neuroimaging Triage: Immediate brain and cervical MRI referral protocol for concerning neurological red flags.
3. Physical Mobility & Flexion-Rotation Test
Flexion-rotation test (FRT) for C1-C2 mobility, upper cervical facet palpation, deep neck flexor endurance, and posture.
- Flexion-Rotation Test (FRT) for C1-C2: Fully flexing cervical spine and passively rotating head (normal rotation is ~44°, reduction indicates C1-C2 dysfunction).
- Upper Cervical Facet Palpation: Digital palpation over C2-C3 articular pillars reproducing headache symptoms.
- Deep Neck Flexor Endurance Test: Testing holding capacity of craniocervical flexion (<20 seconds indicates weakness).
- Suboccipital Muscle Tenderness Check: Palpating rectus capitis posterior and obliquus capitis muscles for hypertonicity.
- Cervical Range of Motion Goniometry: Measuring active rotation, lateral flexion, and extension limits.
- Forward Head Posture Measurement: Assessing tragus-to-wall distance and craniovertebral angle.
- Scapular Dyskinesis Evaluation: Evaluating lower trapezius and serratus anterior support for neck posture.
- Spurling’s Maneuver (Nerve Compression): Ruling out cervical radiculopathy mimicking headache.
- Cervical Distraction Test: Manual axial traction relieving facet compression and headache tension.
- TMJ Jaw Movement Screening: Checking for secondary temporomandibular joint clicking or clenching.
- Physical Baseline Record: Documenting FRT rotation degrees and flexor hold times for rehab monitoring.
4. Cervical Imaging & Care Roadmap
Cervical spine X-rays, MRI, diagnostic medial branch blocks, radiofrequency ablation, and manual therapy.
- Cervical Spine X-Rays (AP, Lateral & Open Mouth): Visualizing C1-C2 alignment, facet arthrosis, and uncovertebral spurs.
- Flexion-Extension Radiographs: Assessing upper cervical segmental instability and ligamentous laxity.
- High-Resolution Cervical MRI: Evaluating spinal canal dimensions, cord compression, and disc herniation.
- Clinical-Radiological Correlation Check: Matching imaging facet degeneration with patient's unilateral headache pattern.
- Diagnostic Medial Branch Blocks (MBB): Fluoroscopic local anesthetic blocks of C2-C3 nerves confirming articular headache source.
- Radiofrequency Ablation (RFA): Thermal neurotomy providing 6-12 months of durable relief for chronic cervicogenic joints.
- Manual Therapy & Joint Mobilization: Skilled physical therapy restoring upper cervical C1-C2 rotational freedom.
- Craniocervical Flexion Training: Biofeedback-guided deep neck flexor strengthening to stabilize upper cervical posture.
- Ergonomic & Workstation Prescription: Adjusting monitor height, chair support, and lighting to eliminate forward head strain.
- Multi-Specialist Pain & Spine Review: Collaborative pain physician, physiatrist, and physical therapist care audit.
- Digital Archiving: Secure storage of headache logs, MBB block response data, and imaging in patient portal.
- Final Clinical Clearance: Approving graduation to independent home posture and neck maintenance routine.
Meet Our Cervicogenic Headache Experts
Our care approach for cervicogenic headaches focuses on assessing neck-related headache patterns, reducing cervical stiffness and muscle tension, improving neck mobility, and addressing posture and movement patterns through an individualized physiotherapy and rehabilitation plan.
Ask Our Specialist
Care is guided by your headache pattern, neck movement, mobility findings, posture, and clinical assessment. An individualized treatment plan may include appropriate physiotherapy, mobility exercises, posture guidance, and rehabilitation to help manage neck-related headaches and support everyday comfort.
Patient Success Stories
Watch real recovery stories from patients who regained their active lifestyles.
Patient Recovery Story
Real experiences. Better mobility.
Patient Recovery Story
Real patient experiences and recovery journeys.
Frequently Asked Questions
Clear answers to common clinical questions about cervicogenic headaches, neck pain, and treatments.